
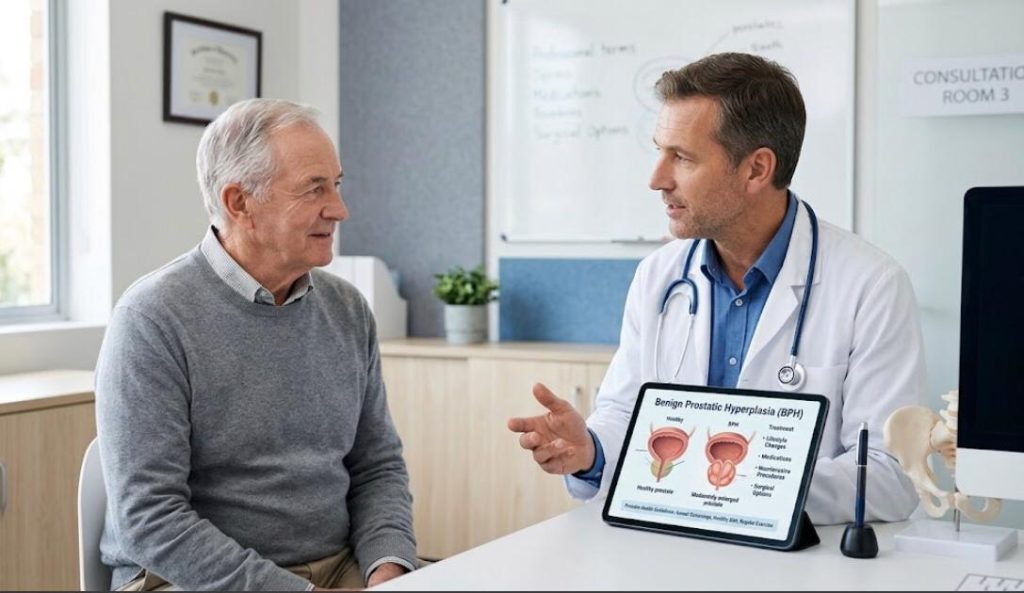
Throughout my fifteen years of clinical practice in urology and internal medicine, the approach to Benign Prostatic Hyperplasia (BPH) has transformed dramatically. We no longer view an enlarging prostate gland as an inevitable, untreatable consequence of male aging. Instead, modern urology treats this condition as a highly manageable, variable metabolic issue.
Men walking into my clinic Abraham Dental Art today face a vastly different landscape than they did even a decade ago. We have moved past the era where invasive surgery was the only definitive answer to urinary retention. Today, managing an enlarged prostate requires a highly personalized matrix of biomarker diagnostics, targeted pharmacotherapy, minimally invasive interventions, and rigorous lifestyle adaptations. This clinical protocol outlines the standard of care as we apply it in 2026, offering actionable, empirically backed strategies drawn directly from contemporary medical practice.
The State of BPH Care in 2026
The contemporary management of lower urinary tract symptoms (LUTS) secondary to BPH heavily relies on early intervention and precise tissue characterization. We categorize prostate enlargement not just by physical volume, but by its distinct anatomical impact on the prostatic urethra and the bladder neck.
Understanding the Modern Clinical Paradigm

Prostate tissue undergoes hyperplasia a cellular proliferation primarily within the transition zone of the gland. This localized growth compresses the urethra, leading to the classic storage and voiding symptoms patients report daily. Current therapeutic models prioritize preserving the structural integrity of the bladder detrusor muscle. If bladder outlet obstruction remains untreated, the detrusor hypertrophies, eventually leading to irreversible fibrous changes and chronic retention.
Diagnostic Shifts in Urological Practice
The days of relying solely on a Digital Rectal Exam (DRE) and a basic Prostate-Specific Antigen (PSA) test are behind us. While I still perform physical examinations to assess prostate symmetry and rule out induration, 2026 protocols integrate high-resolution micro-ultrasound and multiparametric MRI to assess the exact lobe architecture.
When a patient presents with hesitancy or severe nocturia, our immediate objective is mapping the prostate’s specific growth pattern. Is the median lobe protruding directly into the bladder floor? Are the lateral lobes compressing the urethra bilaterally? Identifying this specific morphology dictates the entire treatment trajectory.
Comprehensive Symptom Evaluation and Stratification
Clinical evaluation begins by objectively quantifying the patient’s daily disruption. We rely on the International Prostate Symptom Score (IPSS) as a baseline, but subjective questionnaires only provide half the clinical picture.
Objective data collection is mandatory before prescribing any therapeutic regimen. We measure the maximum urinary flow rate (Qmax) and calculate the post-void residual (PVR) volume using bladder ultrasound. A high PVR indicates that the bladder is failing to empty completely, establishing a direct risk for recurrent urinary tract infections and bladder calculi.
For patients with complex symptoms such as neurogenic bladder overlaps or suspected detrusor underactivity pressure flow urodynamic studies remain the definitive diagnostic tool. By inserting micro catheters to measure bladder pressure during active voiding, I can definitively differentiate between a bladder that is too weak to push and a prostate that is too tight to allow flow.
Home Monitoring Technologies
A significant clinical advantage in 2026 is the integration of at-home uroflowmetry. Many of my patients now use sound-based flow measuring applications on their smartphones or smart-toilet attachments that transmit real-time voiding diaries directly to their electronic health records. This continuous data stream eliminates the “white coat syndrome” often associated with in-clinic voiding tests, allowing me to view a patient’s true functional baseline.
Foundational Treatment Protocols and Efficacy
Treatment algorithms in 2026 are highly stratified. The decision to initiate medical versus surgical therapy hinges on the IPSS score, prostate volume, and the presence of absolute indications for surgery (such as refractory retention or recurrent hematuria).
Below is a breakdown of how we currently position the primary modalities in a modern clinical setting.
Alpha Blockers and Alpha Reductase Inhibitors
Medical management remains the bedrock of initial therapy. By targeting the alpha-1 adrenergic receptors located densely within the prostatic stroma, we can induce rapid muscle relaxation. This reduces urethral resistance without altering the physical size of the gland. Conversely, 5-alpha reductase inhibitors (5-ARIs) modify the disease’s natural history by blocking the conversion of testosterone to dihydrotestosterone (DHT), inducing apoptosis in the epithelial cells and shrinking the prostate over several months.
Acquiring First Line Therapeutics: The Flomax Protocol
In my daily practice, prescribing selective alpha blockers remains the primary intervention for rapid symptom relief. Tamsulosin is the most universally recognized therapeutic agent, and patients frequently request it by name. For individuals managing chronic BPH, maintaining uninterrupted access to this daily medication is highly critical to preventing acute urinary retention. Today, many of my patients choose to buy Flomax online to streamline their treatment regimens. Bypassing the monthly logistical friction of physical pharmacy visits.
When I instruct patients on how to purchase Flomax through digital health portals, I heavily emphasize the necessity of using VIPPS-accredited, legally compliant pharmacies. It is highly convenient and perfectly safe to order Flomax prescriptions via licensed telehealth services, provided a board-certified clinician actively reviews your uroflow metrics, medication interactions, and medical history.
However, attempting to buy prescription Flomax from cheap, unverified international vendors introduces severe risks of counterfeit medication or improper dosing. Always prioritize regulated, state-licensed telemedicine platforms that guarantee drug authenticity. Secure your medical data, and adhere strictly to 2026 FDA dispensing guidelines.
Minimally Invasive Surgical Therapies (MIST)
When pharmacotherapy fails to yield adequate symptom relief. Or if a patient develops adverse effects like orthostatic hypotension or retrograde ejaculation, we escalate to MIST. The proliferation of these technologies has revolutionized outpatient urology.
The goal of MIST is to create a wider urethral channel without the morbidity associated with traditional tissue resection.
Water Vapor Therapy (Rezum)
I frequently utilize convective water vapor therapy for patients with moderate prostate volumes (30-80 grams). By injecting sterile steam directly into the hyperplastic tissue, the thermal energy causes immediate cell death. Over the following weeks, the body naturally resorbs the necrotic tissue, widening the urethra. It is a rapid, 10-minute clinic procedure performed under local anesthesia.
Prostatic Urethral Lifts (UroLift)
For patients strictly prioritizing the preservation of ejaculatory function, mechanical retraction is highly effective. Small permanent implants are deployed to pin back the encroaching lateral lobes, much like opening window curtains. My clinical data reflects excellent immediate flow improvements, though it is not suitable for patients with a prominent obstructive median lobe.
Proper patient selection dictates MIST success. I routinely reject candidates for UroLift if preoperative cystoscopy reveals significant median lobe intravesical prostatic protrusion (IPP), pivoting them instead toward thermal ablation or enucleation.
Advanced Surgical Modalities in 2026
For massive prostate glands (>80 grams) or cases involving total urinary retention, minimally invasive options lack the necessary tissue-removal capacity.
We have largely phased out the traditional Transurethral Resection of the Prostate (TURP) in favor of advanced energy modalities that offer better hemostasis and shorter catheterization times.
HoLEP (Holmium Laser Enucleation of the Prostate)
HoLEP represents the definitive anatomical cure for BPH. Using a holmium laser, I separate the entire adenoma from the surgical capsule, pushing the tissue into the bladder where a morcellator extracts it. Regardless of how massive the prostate has grown even upwards of 200 grams HoLEP provides maximum tissue removal with minimal bleeding risks, making it safe for patients on active anticoagulants.
Aquablation Therapy
One of the most exciting tools in the 2026 surgical arsenal is robotic waterjet ablation. Using real-time ultrasound integration, the surgeon maps the precise contour of the resection zone. A high-velocity, heat-free saline jet then resects the prostatic tissue autonomously. In my experience, Aquablation provides an unparalleled balance of profound symptom relief and the preservation of sexual performance and erectile health as the targeted mapping avoids the ejaculatory ducts and neurovascular bundles completely.
Medical and surgical interventions operate optimally alongside stringent lifestyle modifications. Fluid management and dietary intake heavily influence bladder irritability and pelvic floor tension.
Pro-Prostate vs. Aggravating Dietary Elements
| Dietary Element | Clinical Impact on BPH / LUTS | Recommended Action |
|---|---|---|
| Caffeine (Coffee/Tea) | Acts as a direct diuretic and bladder irritant, exacerbating urgency. | Limit to 1 cup morning only; avoid post-noon. |
| Alcohol | Depresses central nervous system control; increases nighttime urine production. | Restrict intake, completely avoid 4 hours before sleep. |
| Beta-Sitosterol (Pumpkin Seeds) | Mildly anti-inflammatory; supports slight symptom reduction. | Incorporate into daily diet as a supportive measure. |
| Spicy Foods / Capsaicin | Triggers transient bladder wall inflammation in sensitive patients. | Monitor symptoms and eliminate if urgency spikes post-meal. |
| High-Sodium Diets | Drives water retention and subsequent nocturnal diuresis. | Maintain sodium intake below 2,000mg daily. |
Fluid Management Strategies
Volume distribution throughout the day is just as important as the total volume consumed. I instruct my patients to front-load their hydration, consuming the vast majority of their daily water intake before 4:00 PM.
Nocturia waking multiple times at night to void is the most exhausting symptom for my patients. A specific clinical observation I frequently share involves a 62 year old patient who suffered from severe nocturia, waking five times a night. He was resistant to medications. Upon reviewing his habits, we discovered a routine of drinking three cups of green tea between dinner and bedtime. By simply eliminating evening tea and shifting his hydration to the morning, his nocturia dropped to a single episode per night, drastically improving his sleep architecture without a single prescription.
My Clinical Observations and Patient Outcomes

Observing long term disease trajectories shapes my clinical methodology. BPH is not a static condition; it requires dynamic management that shifts as the patient ages and as tissue morphology evolves.
I recently managed a 58 year old executive presenting with severe urinary hesitancy and a weak stream. His initial ultrasound revealed a moderately enlarged prostate (45 grams) with significant lateral lobe compression. He required an immediate return to his high travel schedule and could not tolerate the dizziness associated with high dose alpha blockers.
We opted for a Prostatic Urethral Lift (UroLift). Within two weeks, his Qmax improved from a sluggish 7 mL/s to a robust 18 mL/s. Three years post-procedure, he remains off all daily BPH medications. This highlights a core 2026 tenet: early anatomical intervention often preempts a lifetime of pharmacological dependence.
Navigating Treatment Resistance
Conversely, another segment of my practice involves rescuing patients from failed therapies. When a patient reports that their daily medication no longer works, it usually signals that the physical mass of the prostate has finally overwhelmed the pharmaceutical muscle relaxation.
Adaptive Therapy ModelsIn these scenarios, blindly increasing drug dosages only amplifies side effects. Instead, I repeat the urodynamics and imaging. Transitioning a patient from a failing medical regimen directly to HoLEP or Aquablation stops the cycle of chronic retention and protects the kidneys from retrograde pressure damage.
FAQ: Managing Enlarged Prostate
What are the early signs of an enlarged prostate?
The earliest indicators involve subtle changes in urination patterns, specifically a noticeable delay before the urine stream begins (hesitancy), a stream that stops and starts, and waking up more than once per night to urinate.
Is it safe to buy Flomax online for prostate management?
Yes, you can safely buy Flomax online if you use a state licensed telemedicine platform and a certified digital pharmacy. Ensure that a licensed clinician reviews your symptom scores and medical history before you order Flomax prescriptions, as acquiring medications from unverified overseas websites bypasses critical safety regulations and risks counterfeit exposure.
Can diet alone shrink an enlarged prostate?
Diet cannot physically reduce prostate tissue volume once hyperplastic growth occurs. However, dietary modifications such as eliminating evening caffeine, reducing alcohol intake, and managing sodium can drastically reduce the severity of lower urinary tract symptoms.
Authoritative Scientific Sources
- American Urological Association (AUA) Guidelines: Surgical Management of Benign Prostatic Hyperplasia/Lower Urinary Tract Symptoms. Available at AUAnet.org.
- The Lancet Urology & Nephrology: Long term efficacy of robotic waterjet ablation (Aquablation) compared to TURP for large volume prostate.
- National Institutes of Health (PubMed): Urodynamic profiling and micro ultrasound imaging in the stratification of lower urinary tract symptoms.
- European Association of Urology (EAU): 2026 Standardized protocols for Minimally Invasive Surgical Therapies (MIST) in men with bladder outlet obstruction.