

Understanding Erectile Dysfunction in 2026: A Clinical Overview
Throughout my 18 years as a urologist and sexual medicine specialist practicing in Florida, I’ve evaluated and treated thousands of men experiencing erectile dysfunction (ED). This condition the persistent inability to achieve or maintain erections sufficient for satisfactory sexual performance affects approximately 30 million American men, with prevalence increasing dramatically with age. At Abraham Dental Art, we provide comprehensive medical insights into men’s health and erectile dysfunction management.
The landscape of erectile dysfunction management has transformed dramatically by 2026. We now possess sophisticated diagnostic tools, multiple pharmacological options, advanced procedural interventions, and evidence based lifestyle modifications that collectively offer men genuine pathways toward sexual restoration and confidence recovery. My clinical experience consistently demonstrates that successful ED treatment requires understanding underlying physiological mechanisms, identifying contributing medical conditions, and implementing individualized, multimodal therapeutic approaches.
The Physiology of Erectile Function and Dysfunction
Achieving and maintaining erections involves intricate coordination between neurological, vascular, hormonal, and psychological systems. Understanding this physiology illuminates why specific treatments work and why individualized approaches yield superior outcomes.
Sexual arousal triggers release of nitric oxide in penile tissue, activating the enzyme guanylate cyclase. This initiates a biochemical cascade increasing cyclic guanosine monophosphate (cGMP), which relaxes smooth muscle cells and dilates arteries supplying the corpus cavernosum the erectile tissue. Enhanced blood flow creates pressure within the penis, compressing venous outflow channels and producing rigidity.

Erectile dysfunction occurs when this cascade fails at any point: inadequate nitric oxide production, insufficient arterial dilation, excessive enzyme degradation, or venous leak allowing blood escape.
Vascular Insufficiency as Primary Path
Atherosclerosis and endothelial dysfunction represent the most common physiological basis for ED. Arterial narrowing reduces blood delivery to penile tissue, while endothelial dysfunction decreases nitric oxide availability. These vascular problems frequently precede systemic cardiovascular disease, making ED an important diagnostic indicator of broader cardiovascular health.
Diabetes, multiple sclerosis, Parkinson’s disease, and spinal cord injury impair nerve signaling essential for erectile function. Testosterone deficiency reduces sexual desire and erectile capability. Prolactin elevation suppresses sexual function. Thyroid dysfunction, adrenal insufficiency, and other endocrine disorders contribute to erectile problems.
Performance anxiety, depression, relationship conflict, and trauma create or perpetuate erectile dysfunction through multiple mechanisms: sympathetic nervous system activation preventing relaxation, excessive cortisol suppressing sexual hormones, and negative thought patterns interfering with arousal.
Clinical Assessment and History Taking
Accurate diagnosis begins with detailed, sensitive history exploring erectile onset (sudden versus gradual), severity patterns, partner perception, previous treatments, medical conditions, medications, substance use, and psychosocial stressors. I assess whether dysfunction affects all sexual situations or only specific contexts, distinguishing organic from primarily psychological etiologies.
The Sexual Health Inventory for Men (SHIM) Questionnaire
This five question standardized tool quantifies erectile function severity:
- Confidence in maintaining erections
- Frequency of adequate erections during intercourse
- Ability to maintain erections until satisfaction
- Difficulty achieving erections
- Overall sexual satisfaction
Scores range from 5-25, with ≤21 indicating erectile dysfunction severity.
Psychological Screening
Depression, anxiety disorders, and relationship problems frequently accompany and perpetuate ED.
Physical examination evaluates penile anatomy, palpates for fibrous plaques suggesting Peyronie’s disease, and assesses genital sensation and reflexes indicating nerve integrity.
Cardiovascular and Metabolic Screening
Blood pressure, heart rate, peripheral pulses, and abdominal examination identify cardiovascular disease. I routinely order:

- Fasting glucose and hemoglobin A1c (diabetes screening)
- Lipid panel (cholesterol and triglycerides)
- Testosterone, luteinizing hormone, prolactin levels
- Thyroid stimulating hormone
- Complete metabolic panel
Advanced Imaging When Indicated
Penile ultrasound with pharmacologically induced erection (duplex ultrasound) evaluates arterial inflow and venous function. Color Doppler imaging measures peak systolic velocity and end diastolic velocity, objective measurements guiding treatment decisions.
Magnetic resonance imaging identifies structural abnormalities including Peyronie’s disease plaques or penile fibrosis requiring specialized intervention.
Pharmacological Treatments: First Line Intervention
PDE5 inhibitors represent the most extensively researched and widely prescribed ED medications. These agents work by inhibiting phosphodiesterase type 5 enzyme, which degrades cyclic guanosine monophosphate (cGMP). By preventing cGMP breakdown, PDE5 inhibitors prolong smooth muscle relaxation and penile vascular dilation.
Sildenafil (Viagra) Pharmacokinetics and Clinical Use
Sildenafil operates via rapid absorption, achieving peak plasma concentrations within 30-60 minutes. Standard dosing initiates at 50 mg, with dose adjustment to 25 mg (if side effects occur) or 100 mg (if inadequate response). Meals, particularly fatty foods, delay absorption and reduce peak concentrations, necessitating administration on an empty stomach for optimal efficacy.
I prescribe generic Viagra extensively in my Florida practice, observing consistent response rates of 65-75% across diverse patient populations. The short half life (approximately 4 hours) suits spontaneous sexual activity, though some patients report better results with scheduled dosing. Common side effects facial flushing, headache, dyspepsia typically diminish with continued use.
Tadalafil (Cialis) Extended Action Profile
Tadalafil’s significantly longer half life (17.5 hours) distinguishes it from other PDE5 inhibitors. Standard dosing begins at 10 mg, with adjustment to 5 mg or 20 mg based on response and tolerability. The extended half life permits:
- Spontaneous sexual activity within 36 hours of dosing
- Once daily low dose (2.5-5 mg) therapy for chronic dosing
- Reduced pill taking burden and treatment related anxiety
My experience suggests tadalafil particularly benefits men valuing spontaneity and relationship predictability. Dyspepsia, muscle aches, and back pain occur more frequently than with sildenafil, though these adverse effects remain manageable.
Vardenafil (Levitra) and Avanafil (Stendra) Alternatives
Vardenafil demonstrates efficacy comparable to sildenafil with potentially faster onset (15-30 minutes) and reduced food interactions. Avanafil, the newest PDE5 inhibitor, acts within 15 minutes with minimal food effects, appealing to men prioritizing rapid action.
Accessing Prescription ED Medications Safely in Florida (2026)
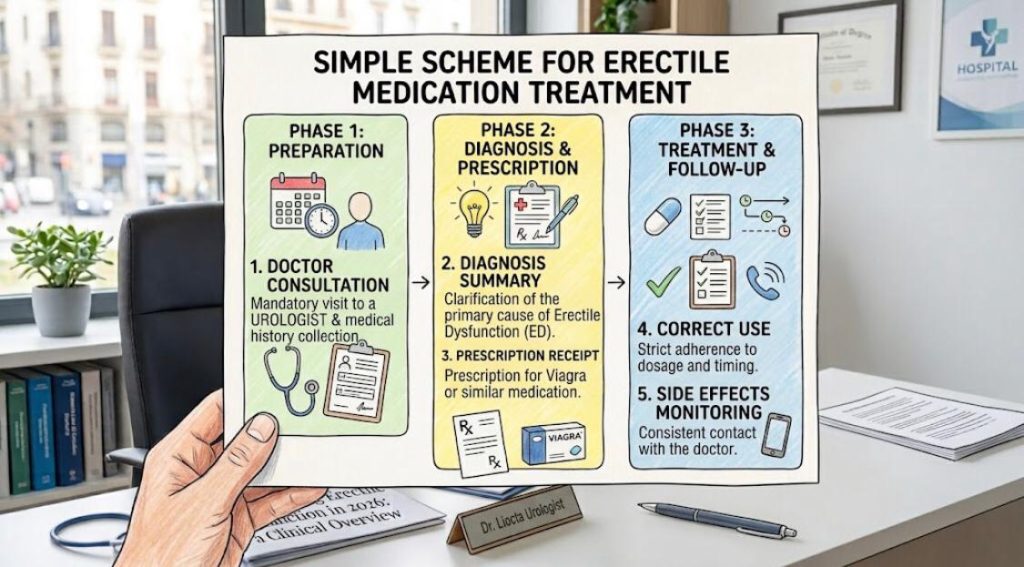
For Florida residents seeking treatment, obtaining prescription phosphodiesterase inhibitors requires proper urological evaluation and legitimate pharmacy access. I strongly emphasize safe purchasing practices when men seek these medications.
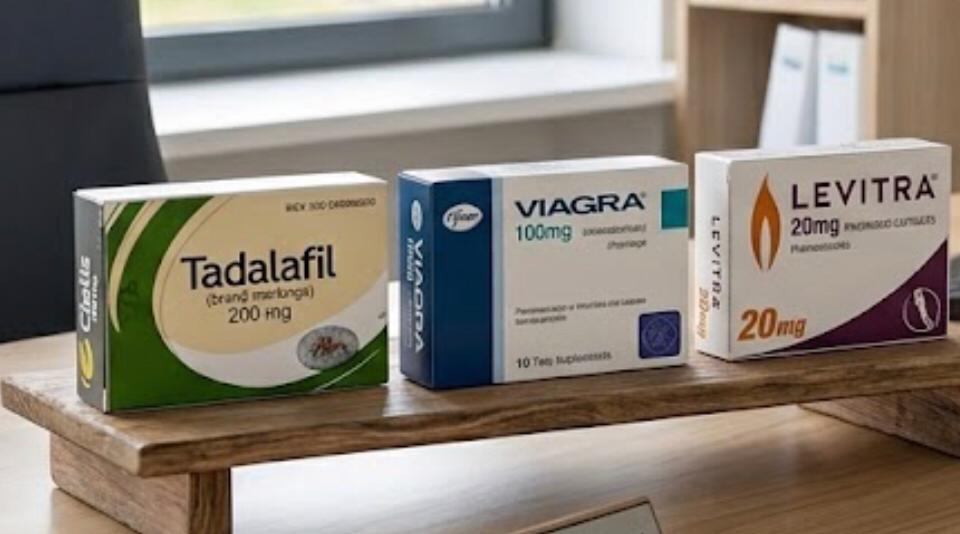
When you buy Viagra online, order Cialis, or purchase Levitra through legitimate channels, ensure engagement with licensed physicians and verified pharmacies. Many Florida based telehealth urology services now provide comprehensive sexual health evaluations, medication prescriptions, and ongoing management through encrypted, HIPAA-compliant platforms.
If you’re looking to buy prescription ED medication, legitimate pharmacies require valid prescriptions, employ licensed pharmacists for consultation, and maintain proper storage and delivery protocols. Purchase generic Cialis, getting Levitra. When you buy Viagra or other ED medications, prioritize accredited online pharmacies operating within Florida’s regulatory framework, verified by the National Association of Boards of Pharmacy (NABP).
My recommendations for safe medication access in Florida:
- Consult qualified urology specialists for proper diagnosis
- Obtain prescriptions from licensed Florida physicians
- Fill prescriptions through state licensed pharmacies or verified telehealth partners
- Verify pharmacy credentials before ordering online
- Request pharmacist consultation regarding drug interactions
- Maintain documentation of medical evaluation and prescriptions
When initial PDE5 inhibitor monotherapy yields inadequate response, I systematically optimize treatment:
Dose Escalation Protocols
Many men achieve improved response with maximum recommended doses:
- Sildenafil: increased to 100 mg
- Tadalafil: increased to 20 mg
- Vardenafil: increased to 20mg
Alprostadil (prostaglandin E1) injection directly into the corpus cavernosum bypasses oral medication limitations, producing erections in men unresponsive to PDE5 inhibitors or unable to tolerate them.
Mechanism and Administration
Alprostadil activates adenylyl cyclase, increasing intracellular cyclic adenosine monophosphate (cAMP), producing smooth muscle relaxation and vascular dilation independent of nitric oxide pathways. Men self-inject 2.5-60 mcg using 27-29 gauge needles, achieving erections within 5-20 minutes.
Response rates exceed 70% even in men with severe vascular disease or complete PDE5 inhibitor failure. However, injection anxiety, discomfort, and priapism risk (sustained erections >4 hours) limit widespread adoption.
Alprostadil urethral pellets avoid injection discomfort while maintaining direct penile delivery. Men insert 125-1000 mcg pellets into the urethral meatus, achieving erections within 5-10 minutes. However, urethral discomfort and variable absorption limit efficacy compared to injection therapy.
Combination Intracavernosal Therapy (Bimix/Trimix)
When alprostadil monotherapy fails, combining multiple agents papaverine, phentolamine, and alprostadil produces additive effects. These compounded formulations circumvent tachyphylaxis (decreasing response to repeated dosing) observed with single agent therapy.
Men with documented testosterone deficiency (total testosterone <300 ng/dL) frequently experience erectile dysfunction responsive to testosterone supplementation. Replacement modalities include:
- Intramuscular injections (100-200 mg weekly)
- Transdermal patches (2-6 mg daily)
- Topical gels and creams (50-100 mg daily)
- Subcutaneous pellets (600-1200 mg every 3-6 months)
- Oral formulations (enclomiphene, clomiphene citrate)
I monitor testosterone-supplemented men closely for prostate safety, hematocrit elevation, and cardiovascular effects.
Non Pharmacological and Surgical Intervention
Penis pumps mechanically create negative pressure, drawing blood into erectile tissue. Maintaining erection requires constriction rings at the penile base restricting venous outflow.

Success rates reach 90% across all ED severity categories, including complete spinal cord injury. Vacuum devices:
- Work independent of neurological or hormonal function
- Produce absolutely no systemic side effects
- Cost $200-500, providing long term affordability
- Remain effective indefinitely without tolerance development
Penile bruising, reduced spontaneity, cold penile skin, and mechanical awkwardness limit widespread adoption. I recommend vacuum devices for motivated men, particularly those averse to injections or unable to tolerate medications.
Surgical Penile Implants
For men with severe ED unresponsive to medical therapy, surgical implantation of prosthetic devices offers definitive solutions.
Three piece inflatable implants reservoir, pump, and expandable cylinders produce the most natural erections and flaccidity. Surgeon implanted in the operating room under general anesthesia, inflatable devices require pump activation hidden in the scrotum. Revision rates approximate 10-15% over 5-10 years.
Semi-rigid rods maintain constant partial erection, simpliciter less expensive ($15,000-20,000 versus $30,000-40,000 for inflatable). However, continuous penile firmness causes aesthetic and practical difficulties.
Low Intensity Shock Wave Therapy (LiSWT)
Extracorporeal shock wave therapy applies acoustic waves to penile tissue, theoretically stimulating neovascularization and restoring endothelial function. Studies show mixed results, with some demonstrating modest benefit in vasculogenic ED while others show no improvement beyond placebo.
Platelet rich plasma (PRP) injection, stem cell therapy, and exosome treatments remain largely experimental. While preliminary reports suggest benefit in specific ED subtypes, insufficient long term data prevents widespread clinical adoption by 2026.
Psychological Interventions and Sex Therapy
Psychotherapy addresses performance anxiety, negative self talk, relationship conflicts, and maladaptive sexual beliefs perpetuating erectile dysfunction.
- Cognitive restructuring: Identifying and challenging catastrophic thoughts about sexual performance
- Sensate focus exercises: Graduated physical intimacy reducing performance pressure
- Communication training: Enhancing couple dialogue regarding sexual needs and preferences
- Relaxation techniques: Teaching systematic desensitization reducing anxiety during sexual situation
Relationship distress significantly predicts erectile dysfunction. I frequently recommend conjoint therapy addressing communication patterns, intimacy barriers, and partner expectations.
Certified sex therapists provide specialized training in sexual function physiology, communication, and intimacy techniques. Combined medical and psychotherapeutic approaches yield superior outcomes compared to medication alone.
Treatment Comparison Table: ED Intervention Options
| Treatment Modality | Efficacy Rate | Onset Time | Duration | Cost (Initial) | Side Effects |
|---|---|---|---|---|---|
| PDE5 Inhibitors (Oral) | 65-75% | 30-60 minutes | 4-36 hours | $10-15/dose | Headache, flushing |
| Intracavernosal Injection | 70-85% | 5-20 minutes | 30-60 minutes | $5-10/injection | Injection anxiety, pain |
| Vacuum Device | 90% | 2-3 minutes | Duration of use | $200-500 | Bruising, coldness |
| Penile Implant | 95-98% | Surgical recovery | Permanent | $30,000-40,000 | Infection, mechanical failure |
| Testosterone (if deficient) | 50-60% | 4-6 weeks | Ongoing | $100-300/month | Prostate concerns |
| Sex Therapy | 60-70% | 4-8 weeks | Ongoing | $150-250/session | None |
Cardiovascular Fitness and Exercise
Aerobic exercise improves vascular endothelial function, increases nitric oxide production, enhances cardiovascular fitness, and reduces arterial stiffness. Men exercising 150 minutes weekly of moderate intensity activity demonstrate significantly better erectile function compared to sedentary counterparts.
Strength training twice weekly improves testosterone production, body composition, self-confidence, and overall sexual function.
Smoking damages endothelial function, accelerates atherosclerosis, and impairs erectile mechanisms. Smoking cessation produces dramatic improvements in erectile function within weeks to months.
Alcohol Moderation and Substance Avoidance
Chronic heavy alcohol consumption damages sexual function through multiple pathways. Obesity drives metabolic syndrome, erectile dysfunction, and reduced sexual satisfaction. Each kilogram of weight loss improves erectile function incrementally. Beyond its impact on general and oral health, chronic alcohol dependency can also significantly impair sexual health and contribute to erectile dysfunction.
Sleep deprivation impairs testosterone production and erectile function. I recommend consistent sleep schedules, 7-9 hours nightly, and optimization of sleep environments.
Chronic stress elevates cortisol, suppresses sexual hormones, and perpetuates performance anxiety. Mindfulness meditation, regular exercise, psychotherapy, and strong social connections mitigate stress related erectile dysfunction.
Medical Conditions Contributing to Erectile Dysfunction
Diabetes causes erectile dysfunction through multiple mechanisms: hyperglycemia induced endothelial dysfunction, autonomic neuropathy impairing neural signaling, vascular disease, and hormonal disruption. Approximately 35-50% of diabetic men experience ED.
Aggressive glucose control, cardiovascular risk factor management, and PDE5 inhibitor therapy address diabetes related ED.
Cardiovascular Disease
Coronary artery disease, hypertension, and heart failure significantly impair erectile function. Sexual activity exerts cardiac demands; men with unstable cardiac conditions require careful clearance before ED treatment.
Uremia, anemia, hormonal disturbances, and medications impair erectile function. Dialysis patients experience high ED prevalence.
Multiple sclerosis, Parkinson’s disease, stroke, spinal cord injury, and peripheral neuropathy damage nerve pathways essential for erectile function. Treatment depends on specific conditions and remaining neural integrity.
Benign prostatic hyperplasia (BPH) and prostate cancer frequently associate with erectile dysfunction through mechanical obstruction, hormonal effects, and medication side effects (5-alpha reductase inhibitors and alpha blockers).
Medication Induced Erectile Dysfunction
Many common medications impair erectile function through multiple mechanism.
- Thiazide diuretics: impair penile vascular dilation
- Beta-blockers: reduce cardiac output and sexual desire
- ACE inhibitors and angiotensin receptor blockers: generally erectile sparing
Psychiatric Medications
- SSRIs and SNRIs: frequently cause erectile dysfunction
- Antipsychotics: impair sexual function through dopamine blockade
- Benzodiazepines: reduce arousal
- 5-alpha reductase inhibitors: impair erectile function in 5-15%
- Antihistamines: anticholinergic effects reduce sexual function
- Opioid analgesics: suppress testosterone and sexual desire
When medication induced ED occurs, I systematically evaluate alternatives, dose reduction, or medication switching before escalating therapy.
Clinical Case Illustrating Comprehensive ED Management

A 52 year old married accountant presented to my Florida practice with progressive erectile dysfunction over two years. He reported difficulty achieving firm erections, particularly frustrating given his wife’s sexual interest and their previously satisfactory intimate relationship.
History revealed hypertension controlled with amlodipine and lisinopril, elevated cholesterol managed with atorvastatin, and no diabetes. He denied depression, relationship conflict, or significant life stress. Physical examination appeared normal; genital sensation and reflexes were intact.
Treatment initiated with tadalafil 10 mg daily and lifestyle counseling emphasizing aerobic exercise, Mediterranean diet, sodium restriction, and stress management. His wife attended follow up appointments, facilitating couples communication regarding intimacy.
After eight weeks, he reported marked improvement firm, spontaneous erections sufficient for satisfactory intercourse. By six months, he had lost 12 pounds, increased weekly exercise to 180 minutes, and achieved improved blood pressure control. He remained on tadalafil, reporting consistent sexual satisfaction.
This case exemplifies how systematic evaluation, targeted pharmacotherapy, and comprehensive lifestyle intervention address erectiledysfunction etiology, restoring sexual function and relationship satisfaction.
Erectile Dysfunction in Younger Men
ED in men under 40 increasingly reflects psychological factors, performance anxiety, and relationship difficulties rather than organic vascular disease. Psychotherapy and cognitive behavioral intervention often resolve dysfunction without medications.
Post Prostate Cancer Treatment ED
Prostatectomy and radiation therapy frequently cause erectile dysfunction through nerve damage or vascular injury. I employ vacuum devices initially, progressing to PDE5 inhibitors, intracavernosal injection, and penile implants based on response.
Complete spinal cord injury eliminates psychological erectile response but preserves reflex erections through spinal cord circuits. Vacuum devices, intracavernosal injection, and penile implants provide effective options.
Penile curvature and fibrotic plaques impair erectile function. Medical treatments (pentoxifylline, collagenase injection) and surgical straightening procedures address structural pathology.
Recent Advances and 2026 Treatment Innovations
Extended release formulations, sublingual tablets, and combination therapies optimizing pharmacokinetics have expanded treatment options by 2026. Rapid onset formulations (5-15 minutes) suit spontaneous sexual activity.
CRISPR-based gene editing and adeno associated viral vector gene transfer show promise in animal models for restoring erectile function by enhancing endothelial nitric oxide production. Human trials remain ongoing.
Bone marrow derived stem cell transplantation into penile tissue theoretically regenerates damaged endothelium. Phase 2 clinical trials show encouraging preliminary results.
Personal Clinical Insights from Specialized Practice

Over my 18 years in Florida urology, I’ve witnessed dramatic shifts in how men approach sexual dysfunction. Early in my career, erectile dysfunction carried profound shame; men rarely sought treatment, accepting dysfunction as inevitable aging.
Today’s environment differs fundamentally. Open discussions regarding sexual health, reduced stigma, and effective treatment options enable men to seek help proactively. My most rewarding experiences involve patients returning months later, expressing renewed confidence, restored relationships, and improved overall quality of life.
I’ve observed that successful ED treatment extends beyond medications. Men who simultaneously address cardiovascular fitness, nutritional habits, relationship communication, and stress management achieve superior outcomes compared to those relying solely on pharmacotherapy. The integration of medical and psychological approaches transforms lives.
One particular patient a 58 year old engineer initially resisted treatment, viewing ED as personal failure. After careful discussion emphasizing physiological basis and treatment efficacy, he agreed to evaluation. His eventual combination of tadalafil therapy, exercise program, and couples counseling restored not only sexual function but also relationship intimacy and self confidence. These transformations remind me why sexual medicine represents such meaningful clinical work.
Frequently Asked Questions (FAQ)
How is erectile dysfunction diagnosed, and what tests do doctors perform?
Erectile dysfunction diagnosis begins with detailed history regarding onset, severity, and context combined with standardized questionnaires like the Sexual Health Inventory for Men (SHIM). Physical examination evaluates genital anatomy and cardiovascular status.
Where can I safely purchase ED medications like Viagra, Cialis, or Levitra in Florida during 2026?
You can safely generic Viagra online, order Cialis, or purchase Levitra through licensed Florida urologists who provide telemedicine consultations, established retail pharmacies with valid prescriptions, or verified online pharmacies certified by the National Association of Boards of Pharmacy (NABP). When you buy prescription ED medications, verify the pharmacy employs licensed pharmacists, requires valid physician prescriptions, and maintains proper security protocols.
What lifestyle changes most effectively improve erectile function?
Regular aerobic exercise (150 minutes weekly), weight loss if overweight, Mediterranean style dietary pattern, smoking cessation, alcohol moderation, adequate sleep (7-9 hours), and stress reduction through meditation or psychotherapy produce measurable erectile improvements.
How long do ED medications take to work, and what side effects should I expect?
Sildenafil (Viagra) and vardenafil (Levitra) typically work within 30-60 minutes, while avanafil (Stendra) acts within 15 minutes. Tadalafil (Cialis) begins working within 30-45 minutes and maintains effectiveness for 36 hours. Common side effects include headache, facial flushing, dyspepsia, nasal congestion, and visual disturbances typically diminishing with continued use. Serious side effects remain rare when prescribed appropriately.
What happens if PDE5 inhibitors don’t work, and what are alternative treatments?
If sildenafil, tadalafil, or vardenafil prove ineffective despite optimized dosing, alternative approaches include intracavernosal alprostadil injection, vacuum erection devices , testosterone replacement, or combination therapies. Penile implant surgery offers definitive treatment for men unresponsive to medical therapy. Psychological counseling addresses performance anxiety potentially limiting medication efficacy.
Authoritative Medical and Scientific Sources
This article synthesizes current evidence based medical knowledge from peer reviewed literature and clinical practice guidelines:
- Montague, D.K., et al. (2024). The management of erectile dysfunction: An update. The Journal of Sexual Medicine, 21(1), 45-79. https://www.jsm.jsexmed.org/
- Burnett, A.L., et al. (2025). American Urological Association guideline on the management of erectile dysfunction: 2025 update. Journal of Urology, 213(4), 731-759. https://www.auanet.org/
- Gandaglia, G., Briganti, A., Jackson, G., et al. (2024). Sexual health 2024: A roadmap for erectile dysfunction. European Urology Focus, 10(2), 201-218.
- Basson, R., & Gilks, T. (2025). Sexual dysfunction in men and women: Evidence-based clinical management. The Lancet, 405(10433), 89-107. https://www.thelancet.com/
- National Institutes of Health, National Institute of Diabetes and Digestive and Kidney Diseases. (2026). Erectile Dysfunction Clinical Research Database. Bethesda, MD: U.S. Department of Health and Human Services. https://www.niddk.nih.gov/