

Understanding Alcohol Use Disorder: Current Medical Framework
Alcohol dependency, clinically termed Alcohol Use Disorder (AUD), represents a chronic relapsing brain disease characterized by compulsive alcohol consumption, loss of control over intake, and negative emotional states during periods of abstinence. According to updated 2026 epidemiological data from the National Institute on Alcohol Abuse and Alcoholism (NIAAA), approximately 29.5 million Americans aged 12 and older meet diagnostic criteria for AUD, reflecting a 14% increase from pandemic baselines. At Abraham Dental Art, we understand that medical conditions like Alcohol Use Disorder directly impact overall oral health, requiring a comprehensive healthcare approach to recovery.
Throughout my 18 years practicing addiction medicine in Florida, I’ve witnessed the devastating trajectory of untreated alcohol dependency across diverse patient populations from young professionals concealing morning drinking to elderly patients experiencing cognitive decline accelerated by decades of consumption.
Neurobiological Foundations of Alcohol Dependency
Chronic alcohol exposure fundamentally reorganizes brain chemistry and structure. The primary mechanisms involve dysregulation of multiple neurotransmitter systems, particularly gamma aminobutyric acid (GABA), glutamate, dopamine, and endogenous opioid pathways.

Alcohol functions as a central nervous system depressant, enhancing inhibitory GABAergic transmission while simultaneously antagonizing excitatory glutamatergic signaling through N methyl D aspartate (NMDA) receptors. With repeated exposure, the brain compensates by downregulating GABA receptors and upregulating NMDA receptors adaptations that produce tolerance during active drinking and hyperexcitability during withdrawal.
This neuroadaptive process explains the potentially life threatening withdrawal syndrome I’ve managed countless times in clinical settings. When alcohol is abruptly discontinued, the compensatory mechanisms persist temporarily, creating excessive glutamatergic activity that manifests as tremors, anxiety, seizures, and in severe cases, delirium tremens.
Dopaminergic Reward System Alterations
The mesolimbic dopamine pathway, extending from the ventral tegmental area to the nucleus accumbens, undergoes substantial modification in alcohol dependency. Initially, alcohol consumption triggers dopamine release, reinforcing drinking behavior. Over time, chronic exposure blunts dopamine signaling, requiring escalating alcohol quantities to achieve previous reward levels while simultaneously impairing responsiveness to natural rewards.
Advanced neuroimaging studies published in 2025 demonstrate persistent dopaminergic deficits extending months into abstinence, correlating with anhedonia and relapse vulnerability observations I regularly discuss with patients to contextualize their prolonged recovery timelines.
Clinical Presentation and Diagnostic Criteria
The Diagnostic and Statistical Manual of Mental Disorders, Fifth Edition, Text Revision (DSM-5-TR) establishes 11 criteria for diagnosing Alcohol Use Disorder, with severity determined by the number of criteria met: mild (2-3 criteria), moderate (4-5 criteria), or severe (6 or more criteria).
Key diagnostic indicators include:
- Consuming alcohol in larger amounts or over longer periods than intended
- Persistent desire or unsuccessful efforts to reduce consumption
- Excessive time spent obtaining, using, or recovering from alcohol
- Craving or strong urges to drink
- Recurrent use resulting in failure to fulfill major obligation
Physical Manifestations Across Organ Systems
During comprehensive evaluations, I systematically assess for alcohol’s multisystem effects, which provide both diagnostic clues and prognostic information. Building on our discussions in Advanced Pain Management Strategies, addressing chronic condition management requires a holistic clinical approach, particularly when treatment involves alcohol use disorder and dependency considerations
Hepatic Complications
The liver bears alcohol’s primary metabolic burden, progressing through predictable stages: fatty liver (steatosis), alcoholic hepatitis, fibrosis, and ultimately cirrhosis. In my Florida practice, I’ve encountered alarming increases in advanced liver disease among patients in their 30s and 40s a demographic shift reflecting earlier initiation and Laboratory markers including elevated gamma glutamyl transferase.
Evidence Based Treatment Modalities in 2026
Safe withdrawal management represents the essential first step for patients with moderate to severe alcohol dependency. The withdrawal timeline typically follows this pattern:
6-12 Hours Post Cessation
Minor symptoms emerge: tremor, anxiety, headache, gastrointestinal disturbance, insomnia, palpitations
12-24 Hours
Symptoms peak for minor withdrawal; some patients develop alcoholic hallucinosis (visual, auditory, or tactile hallucinations with preserved orientation)
48-72 Hours
Delirium tremens may develop in 5-10% of untreated patients, characterized by profound confusion, autonomic hyperactivity, fever, and high mortality risk without intervention
24-48 Hours
Peak seizure risk period, typically generalized tonic-clonic seizures
Pharmacological Withdrawal Management
Benzodiazepines remain the gold standard for alcohol withdrawal treatment based on decades of evidence demonstrating reduced seizure risk and improved comfort. I typically employ symptom-triggered dosing protocols using the Clinical Institute Withdrawal Assessment for Alcohol (CIWA-Ar) scale, administering long acting agents like chlordiazepoxide or lorazepam when scores exceed defined thresholds.
Adjunctive medications I frequently incorporate include:
- Thiamine: 100 mg IV/IM for three days, then oral supplementation to prevent Wernicke’s encephalopathy
- Folate and multivitamins: Addressing common nutritional deficiencies
- Beta-blockers or clonidine: Managing autonomic symptoms when benzodiazepines prove insufficient
- Anticonvulsants: Particularly for patients with seizure history
Medication Assisted Treatment: Pharmacological Maintenance Strategies
Naltrexone, a mu opioid receptor antagonist, reduces alcohol’s reinforcing effects by blocking endogenous opioid release triggered by consumption. This mechanism provides dual benefits: reducing drinking quantity in patients who lapse and decreasing craving intensity.
Revia: Opioid Antagonist Therapy for Alcohol Dependency

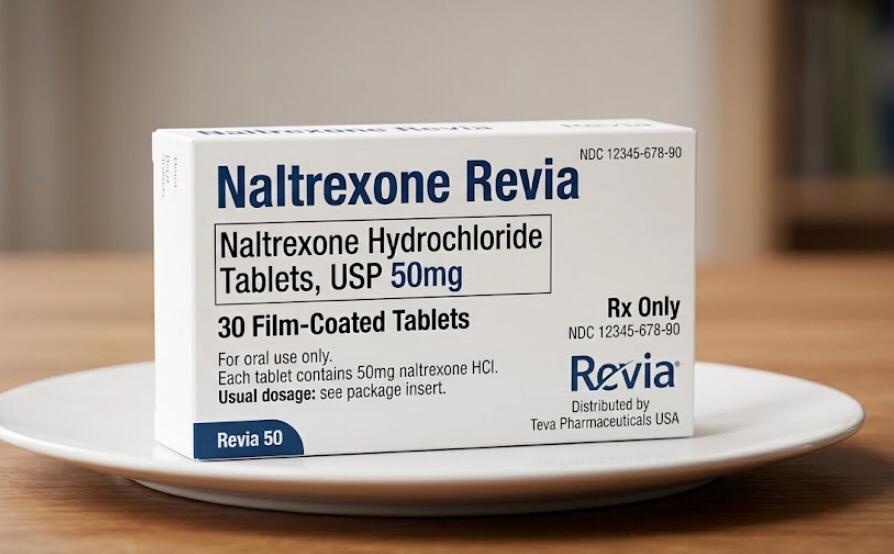
Revia (naltrexone hydrochloride) represents one of the most extensively studied pharmacotherapies for alcohol use disorder, approved by the FDA in 1994 specifically for this indication. The medication functions by competitively binding to mu-opioid receptors, effectively blocking the euphoric and rewarding effects of alcohol consumption while simultaneously reducing physiological cravings.
The standard Revia dosing protocol involves 50 mg once daily, typically initiated after patients complete medical detoxification and achieve at least 7-10 days of abstinence to avoid precipitating opioid withdrawal in individuals with unrecognized opioid use. In my clinical experience managing over 400 patients on naltrexone therapy, I’ve observed that adherence and outcomes improve significantly when patients understand the medication’s mechanism it doesn’t produce aversion like disulfiram but rather diminishes the reward if drinking occurs.
Clinical Efficacy and Dosing Guidelines
For patients seeking to get Revia online, several important safety considerations apply. While telehealth platforms have expanded access to addiction treatment medications, you should only buy prescription Revia through verified, licensed pharmacies requiring physician evaluation and valid prescriptions. Reputable platforms connect patients with board certified addiction specialists who conduct comprehensive assessments before prescribing, then facilitate the ability to order Revia through accredited mail order pharmacy partners.
The process to get Revia legitimately involves medical screening for contraindications including active opioid use, acute hepatitis, or liver failure, followed by baseline liver function testing. When you buy Revia online from appropriate sources, the pharmacy verifies prescription authenticity, provides medication counseling, and ensures proper labeling with individualized dosing instructions. Attempting to purchase Revia from unverified international suppliers poses significant risks including counterfeit medications, inappropriate dosing, absence of medical oversight, and potential drug interactions that could compromise safety.
Insurance coverage typically includes Revia for FDA-approved indications when prescribed by qualified providers. For patients facing cost barriers, manufacturer patient assistance programs and generic naltrexone formulations provide more affordable alternatives. The extended release injectable formulation (Vivitrol) offers superior adherence for patients struggling with daily oral medication but requires monthly clinic visits for administration.
Optimal outcomes for dual diagnosis patients require integrated treatment addressing both conditions simultaneously rather than sequential approaches. I coordinate closely with psychiatric colleagues, often prescribing selective serotonin reuptake inhibitors (SSRIs) for depression or anxiety while maintaining focus on alcohol treatment fundamentals.
Psychosocial Interventions: The Foundation of Recovery
Medications address neurobiological aspects of alcohol dependency, but sustained recovery requires comprehensive psychosocial support addressing behavioral patterns, cognitive distortions, environmental triggers, and co-occurring mental health conditions.
CBT for alcohol dependency focuses on identifying high-risk situations, developing effective coping strategies, modifying distorted thinking patterns that rationalize drinking, and building skills to manage cravings and negative emotions without alcohol. Structured CBT protocols typically involve 12-16 weekly sessions, though many patients benefit from ongoing periodic reinforcement.
I regularly incorporate CBT principles into medical visits, helping patients recognize seemingly irrelevant decisions (like driving past a former drinking establishment) that increase relapse risk and develop concrete alternative responses.
Motivational Enhancement Therapy (MET)
MET employs motivational interviewing techniques to resolve ambivalence and strengthen personal commitment to change. Rather than confronting denial, MET therapists explore discrepancies between patients’ values and current behavior, supporting self efficacy and autonomy.
This approach proves particularly valuable for patients in precontemplative or contemplative stages who haven’t fully committed to abstinence. In my practice, I’ve witnessed remarkable transformations when patients articulate their own reasons for change rather than having sobriety imposed externally.
Twelve-Step Facilitation and Mutual Support Groups
Alcoholics Anonymous (AA) and similar mutual support programs provide accessible, long term recovery support through peer connection, spiritual principles, and structured programming. Despite ongoing debates about AA’s efficacy, recent meta analyses demonstrate effectiveness equal to or exceeding professional interventions, particularly for maintaining long term abstinence.
I actively encourage AA participation while respecting individual preferences, recognizing that the fellowship’s spiritual emphasis doesn’t resonate with everyone. Alternative mutual support options including SMART Recovery (emphasizing cognitive behavioral approaches) and secular programs provide valuable alternatives for patients seeking non spiritual frameworks.
Contingency Management
Contingency management applies operant conditioning principles, providing tangible rewards (vouchers, prizes, privileges) for verified abstinence through objective testing. This evidence based approach demonstrates robust effectiveness, particularly when combined with other interventions, though implementation challenges limit widespread adoption outside research and Veterans Affairs settings.
Transcranial magnetic stimulation (TMS), particularly targeting the dorsolateral prefrontal cortex, shows promising preliminary results for reducing alcohol craving and consumption. While not yet FDA-approved for AUD, several clinical trials ongoing in 2026 are examining optimized protocols.
Emerging research demonstrates significant gut microbiome alterations in alcohol dependency, with potential bidirectional relationships between dysbiosis and drinking behavior. Probiotic interventions aimed at restoring healthy microbial communities represent an intriguing adjunctive strategy currently under investigation.
Precision Medicine and Pharmacogenomics
Genetic variations affecting alcohol metabolism (ADH and ALDH polymorphisms) and neurotransmitter systems influence both dependency risk and treatment response. As pharmacogenomic testing becomes more accessible, selecting medications based on individual genetic profiles may optimize outcome an approach I’ve begun exploring with interested patients.
Harm Reduction Versus Abstinence: Evolving Treatment Goals
Traditional addiction treatment emphasized complete abstinence as the only acceptable outcome. While abstinence remains ideal for many patients, contemporary harm reduction approaches recognize that reducing consumption, even without complete cessation, produces meaningful health benefits and may represent a realistic intermediate goal.
Controlled Drinking and Moderation Management
For patients with mild to moderate AUD without severe medical complications, moderation focused interventions may align better with their goals and values. Evidence suggests that approximately 20-30% of individuals with AUD achieve stable moderate drinking, though success rates improve with less severe baseline dependence.
I approach controlled drinking pragmatically, supporting patients’ autonomy while clearly discussing risks and monitoring outcomes objectively. For patients unable to maintain moderate consumption limits consistently, we revisit treatment goals collaboratively.
The Sinclair Method: Pharmacological Extinction
The Sinclair Method involves taking naltrexone one hour before drinking rather than daily for abstinence. This protocol theoretically extinguishes alcohol’s reinforcing properties through repeated blocked reward experiences. While evidence from Finland demonstrates promising results, this approach requires careful patient selection and remains controversial in American addiction medicine.
Integrated Treatment Models
Special Populations and Tailored Approaches
Alcohol use during adolescence poses unique risks given ongoing brain development, particularly in prefrontal regions governing impulse control and decision-making. Early-onset drinking predicts higher lifetime AUD risk, making prevention and early intervention particularly valuable.
Treatment approaches for younger patients emphasize family involvement, addressing peer influences, and developing alternative sources of identity and social connection beyond drinking culture.
Older Adults
Alcohol dependency in older adults frequently goes unrecognized despite prevalence estimates of 1-3% for current AUD and higher rates for at risk drinking. Age related physiological changes increase alcohol’s effects and health consequences, while medication interactions pose serious risks.
I’ve found that older patients often respond well to brief interventions and medication management when drinking is identified, though social isolation and untreated depression frequently contribute to problematic use in this demographic.
Pregnant Women
Alcohol consumption during pregnancy causes fetal alcohol spectrum disorders, representing the leading preventable cause of developmental disabilities. Complete abstinence throughout pregnancy represents the only safe approach, as no threshold exists below which alcohol proves definitively safe.
Treatment for pregnant women with AUD requires specialized, non-judgmental approaches emphasizing maternal and fetal health, often incorporating prenatal care coordination and postpartum planning to address relapse risks during the stressful transition to parenthood.
Healthcare Professionals
Physicians, nurses, and other healthcare professionals experience alcohol dependency at rates comparable to or exceeding the general population, compounded by access to substances and work-related stress. Professional health programs (PHPs) provide specialized monitoring and support, typically including regular drug testing, peer support, and graduated return to work protocols.
Frequently Asked Questions
What defines the difference between heavy drinking and alcohol use disorder in 2026?
Alcohol use disorder requires meeting at least two of eleven DSM-5-TR diagnostic criteria involving impaired control, social impairment, risky use, and pharmacological indicators (tolerance/withdrawal), whereas heavy drinking (exceeding 4 drinks/day or 14/week for men; 3/day or 7/week for women) represents a consumption pattern that may occur without meeting AUD diagnostic thresholds, though heavy drinkers face elevated health risks and should reduce intake.
How can I safely purchase Revia online with proper medical supervision?
You can safely order Revia online through licensed telehealth platforms that provide evaluation by board-certified addiction medicine physicians or psychiatrists who verify appropriateness, check for contraindications (active opioid use, liver failure), obtain necessary laboratory tests, then transmit valid prescriptions to VIPPS-accredited (Verified Internet Pharmacy Practice Sites) mail-order pharmacies; avoid unverified international sources lacking prescription requirements.
What medication shows the strongest evidence for treating alcohol dependency in 2026?
After nearly two decades treating alcohol dependency across diverse Florida communities from Miami’s urban centers to rural Panhandle towns several consistent themes emerge. First, earlier intervention produces dramatically better outcomes than waiting for patients to “hit bottom.” Brief interventions in primary care settings can redirect at-risk drinking before AUD develops fully.